

Each kind of evidence answers one question, and a long history of use answers none of them alone
Absorption versus benefit, dose and exposure, herb–drug interactions measured in people, safety margins and the drug pathway, each from cited published studies. EUTECNIQ's role is a proposal.
Status. EUTECNIQ Sciences is a company in formation with no studies or data of its own. The results on this page are published third-party studies; the evidence standard and services described are proposals.
Academy fundamentals: Course 1, History of botanical medicine · Course 8, Solubility, pH and the body · Course 9, Toxicology and dose
In a phase I study, quadrupling a single EGCG dose raised its AUC about sevenfold, not fourfold
Dose rose 4-fold (200 to 800 mg); mean AUC rose 7.4-fold for both formulations (22.5 to 167.1 and 21.9 to 161.4 min·µg/mL).
Data table
| Dose (EGCG content) | EGCG: AUC, min·µg/mL | Polyphenon E: AUC, min·µg/mL | EGCG: per 100 mg (derived) | Polyphenon E: per 100 mg (derived) |
|---|---|---|---|---|
| 200 mg | 22.5 | 21.9 | 11.25 | 10.95 |
| 400 mg | 35.4 | 52.2 | 8.85 | 13.05 |
| 600 mg | 101.9 | 79.7 | 16.98 | 13.28 |
| 800 mg | 167.1 | 161.4 | 20.89 | 20.18 |
A fold-change measured at one dose does not transfer to another dose, and dose-normalized comparisons assume a proportionality this study did not find.
Explanation, details and sources
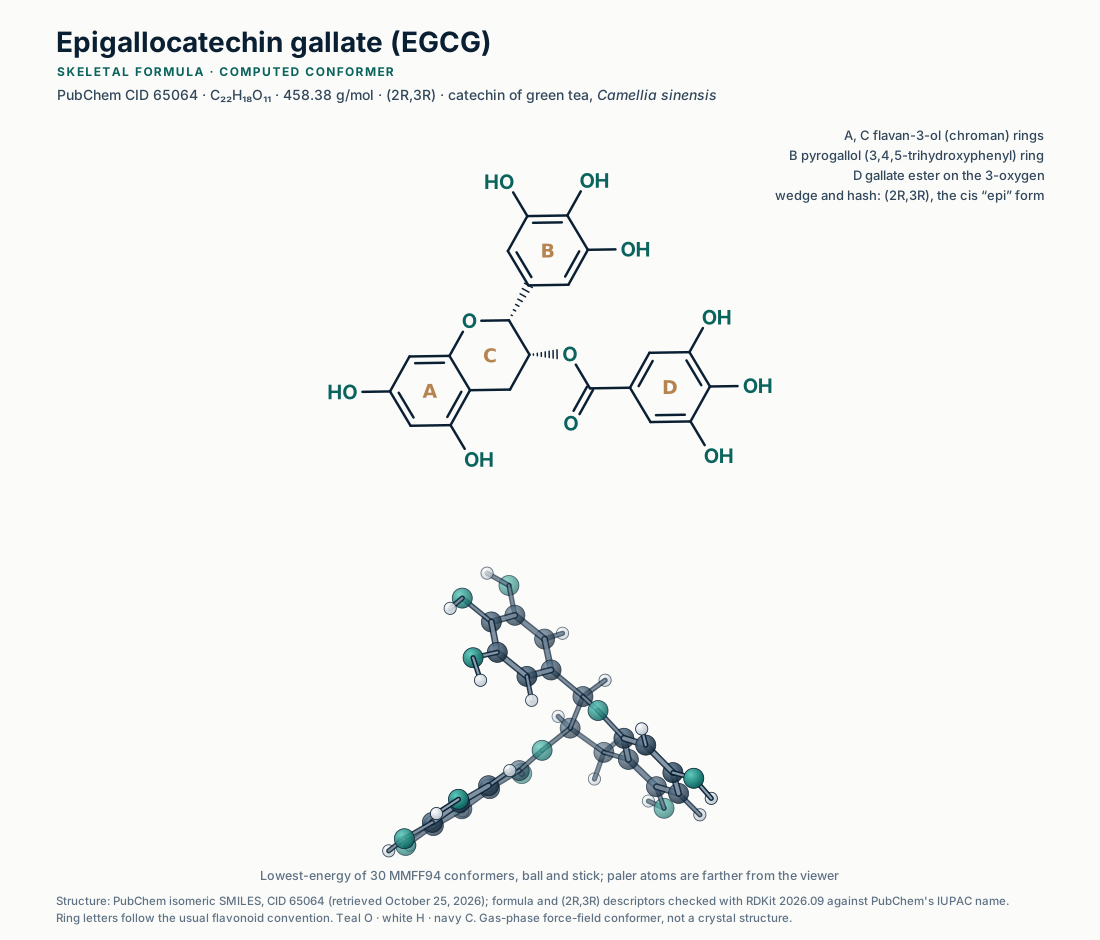
The same group reported a more than 60% increase in the AUC of free EGCG after 4 weeks of 800 mg once daily, but no significant change at 400 mg twice daily (Chow et al. 2003), and a more than 3.5-fold higher average Cmax of free EGCG when Polyphenon E was taken after an overnight fast rather than with a light breakfast (Chow et al. 2005). Dose, schedule and food each changed exposure to the same ingredient.
EFSA concluded that EGCG intakes of at least 800 mg/day from supplements increased serum transaminases in intervention trials (EFSA 2018; see the safety-margin section below). How dose, form and genetic susceptibility appear in documented botanical harms is set out on Lessons learned.
Chow HH, et al. Clin Cancer Res. 2003;9:3312–3319. Chow HH, et al. Clin Cancer Res. 2005;11:4627–4633. EFSA ANS Panel. EFSA J. 2018;16(4):e05239.
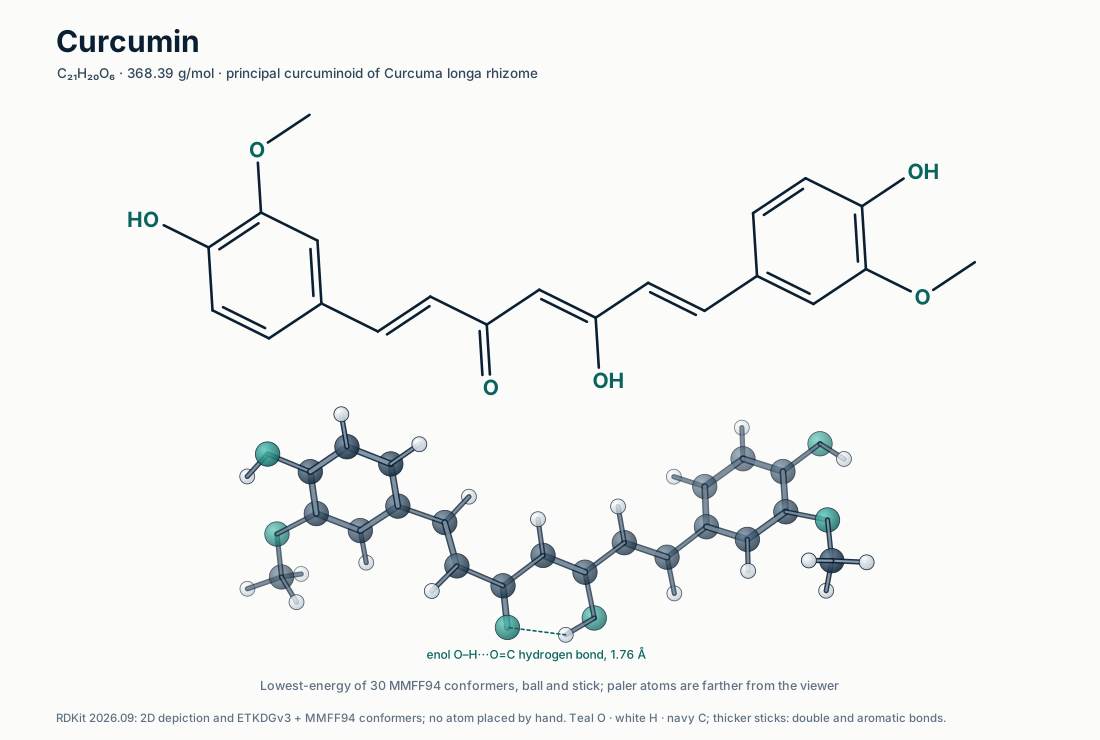
Unformulated curcumin was undetectable in serum up to 8 g and found in 2 of the 6 volunteers given 10 or 12 g
Data table
| Dose | Subjects with detectable serum curcumin | Baseline, ng/mL | 1 h | 2 h | 4 h |
|---|---|---|---|---|---|
| 0.5, 1, 2, 4, 6 and 8 g | 0 of 3 at each dose | No curcumin detected | |||
| 10 g | 1 of 3 | approx. 6.0 | 30.4 | 39.5 | 50.5 |
| 12 g | 1 of 3 | approx. trace | 29.7 | 57.6 | 51.2 |
Undetectable parent compound reflects the analyte and the assay; conjugated curcumin metabolites were found in every subject given 10 or 12 g (Vareed et al. 2008).
Explanation, details and sources
At 10 and 12 g, free curcumin was detectable in only one of 12 subjects at any of 14 time points (assay limit 50 ng/mL), while curcumin glucuronides and sulfates were found in all of them (Vareed et al. 2008). After 0.5 to 5 g of resveratrol, peak levels of two monoglucuronides and resveratrol-3-sulfate were 3- to 8-fold higher than those of resveratrol, and their AUCs up to 23 times greater (Boocock et al. 2007). With a radiolabeled 25 mg dose, at least 70% of resveratrol was absorbed, yet unchanged resveratrol stayed below 5 ng/mL while resveratrol plus metabolites peaked at 491 ± 90 ng/mL (Walle et al. 2004).
A tracer study that counted every labeled product of an anthocyanin is charted on Bioavailability by design.
Vareed SK, et al. Cancer Epidemiol Biomarkers Prev. 2008;17:1411–1417. Boocock DJ, et al. Cancer Epidemiol Biomarkers Prev. 2007;16:1246–1252. Walle T, et al. Drug Metab Dispos. 2004;32:1377–1382.
Release in the gut, absorption, exposure, activity at a target and benefit in a trial are five different results
Text version of the five terms
- Bioaccessibility
- The fraction released from the food or product matrix into the digestive fluid and available for absorption. Measured in vitro, for example with the INFOGEST digestion protocol.
- Bioavailability
- "The rate and extent to which the active ingredient or active moiety is absorbed from a drug product and becomes available at the site of action" (21 CFR 320.1). Measured in people from blood concentrations.
- Exposure
- The concentration–time profile of the relevant compound or metabolite (Cmax, AUC) at the dose taken. It depends on dose and bioavailability, and drives both effects and toxicity.
- Pharmacodynamic activity
- A measurable biological response at the achieved exposure, such as enzyme inhibition or a biomarker change. It shows mechanism, not benefit.
- Clinical efficacy
- A benefit on a clinical or validated endpoint in a controlled human study, for the population, dose and duration studied.
Explanation, details and sources
Bioavailability claims go wrong when one result is reported as another. Each is measured differently and is necessary but not sufficient for the next.
Six evidence steps decide whether a botanical becomes a product, and each answers only its own question
| Product type | 1 · Chemistry | 2 · Reproducibility | 3 · Formulation | 4 · Safety | 5 · Human evidence | 6 · Manufacture |
|---|---|---|---|---|---|---|
| Dietary supplement | Required: identity and specifications (Part 111) | Required: each batch meets specifications | EUTECNIQ standard | Law: new dietary ingredients only; EUTECNIQ standard | Claim substantiation | Required: Part 111 |
| Drug | Required | Required | Required | Required | Controlled trials and FDA approval (partners) | Drug cGMP through CDMOs |
Explanation, details and sources
Traditional use sits before step 1: it points to candidates but does not establish identity, dose, consistency, safety or efficacy.
- Step 1
Chemistry
- Establishes
- Identity; actives measured
- Does not establish
- Reproducibility
- How
- LC-MS, HPTLC, marker assays
- Step 2
Reproducibility
- Establishes
- Composition within justified specifications
- Does not establish
- Stability in a product
- How
- Standardized extraction; methods validated per ICH Q2(R2)
- Step 3
Formulation
- Establishes
- A stable, dosable product
- Does not establish
- Absorption in people
- How
- Emulsions, encapsulation, drying; stability studies
- Step 4
Safety
- Establishes
- Toxicology and exposure margins
- Does not establish
- Efficacy
- How
- NDI and GRAS dossiers; IND-enabling nonclinical data (ICH M3(R2))
- Step 5
Human evidence
- Establishes
- Human data for a defined claim and dose
- Does not establish
- Other claims or doses
- How
- INFOGEST screening, then pharmacokinetics and trials with clinical partners
- Step 6
Manufacture
- Establishes
- Released product, lot after lot
- Does not establish
- A new claim
- How
- Part 111 release; drug GMP placed with qualified CDMOs
Strength of evidence is a judgment about a body of studies, graded down for bias, inconsistency, indirectness, imprecision and publication bias
Text version: certainty levels, rating factors, effect sizes and bias
| Level | Meaning for a reader |
|---|---|
| High | Very confident that the true effect lies close to the estimate |
| Moderate | Moderately confident: the true effect is likely to be close to the estimate, but may be substantially different |
| Low | Limited confidence: the true effect may be substantially different from the estimate |
| Very low | Very little confidence: the true effect is likely to be substantially different from the estimate |
| Direction | Factor |
|---|---|
| Down | Risk of bias; inconsistency between studies; indirectness (other population, dose, product or endpoint); imprecision (wide confidence intervals, few events); publication bias |
| Up (mainly observational evidence) | A large effect (at least a two-fold change in risk); a dose–response gradient; plausible confounding that would reduce the observed effect |
Guyatt GH et al. BMJ. 2008;336:924–926. Balshem H et al. GRADE guidelines: 3. Rating the quality of evidence. J Clin Epidemiol. 2011;64(4):401–406. Guyatt GH et al. GRADE guidelines: 9. Rating up the quality of evidence. J Clin Epidemiol. 2011;64(12):1311–1316. Level meanings paraphrase Table 5.1 of the GRADE Handbook (GRADE Working Group).
An effect size means little without its uncertainty, its sample and the risk of bias in the study that produced it
Report the difference, not only the p-value
A study should report the estimated difference between groups with its 95% confidence interval: an absolute difference (for example, percentage points of responders) and, where useful, a relative one (a risk ratio). A standardized mean difference, the difference divided by the standard deviation, lets different scales be compared but hides the clinical meaning.
Small studies overstate effects
Low statistical power reduces the chance of detecting a true effect and also the chance that a significant result reflects one. Significant results from small studies therefore tend to overestimate effect sizes (Button et al. 2013). A wide confidence interval is the honest signal of imprecision.
Sample-size calculators →Five places a randomized trial can go wrong
The Cochrane RoB 2 tool assesses bias arising from the randomization process, from deviations from intended interventions, from missing outcome data, in measurement of the outcome and in selection of the reported result. Unblinded outcome assessment, missing outcome data and selective reporting are typical concerns these domains capture.
Button KS et al. Nat Rev Neurosci. 2013;14(5):365–376. Sterne JAC et al. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019;366:l4898.
An effect size needs its 95% confidence interval, its sample and its risk of bias; small studies tend to overstate effects.
Explanation, details and sources
Traditional preparations, supplements, isolated compounds and botanical drugs are different products, and traditional leads became drugs as purified molecules
Text version of the six routes
- Lead + method
Artemisinin from Qinghao (Artemisia annua)
Ge Hong's fourth-century instruction to soak qinghao in cold water pointed Tu Youyou's team to low-temperature extraction. Tu 2011, Nat Med
- Lead (mineral)
Arsenic trioxide from Folk arsenic preparation
Investigated by Chinese clinicians and used in acute promyelocytic leukemia since the early 1990s. Wang & Chen 2008, Blood
- Chemical lineage
Metformin from Goat's rue (Galega officinalis)
A guanidine-rich European remedy led to guanidine derivatives; metformin itself is synthetic. Bailey 2017, Diabetologia
- Scaffold lineage
Cromolyn (1965) · amiodarone from Ammi visnaga
Khellin, a long-used smooth-muscle relaxant, was modified into new drugs. Edwards 2014; Shah & Bharate 2024
- Serendipity
Vinblastine · vincristine from Catharanthus roseus
Testing a folk antidiabetic use, which proved wrong, revealed anticancer alkaloids. Noble 1990, Biochem Cell Biol
- Screening
Paclitaxel from Pacific yew (Taxus brevifolia)
Found by systematic plant screening, not by traditional use. Wani et al. 1971, J Am Chem Soc
Show data
| Origin (Newman & Cragg category) | Share of 1,881 approvals | Squares (rounded) |
|---|---|---|
| Unaltered natural product (N) | 3.8% | 4 |
| Natural-product derivative (ND) | 18.9% | 19 |
| All other origins | 77.3% | 77 |
Explanation, details and sources
One plant can appear in all four categories. Green tea is drunk as an infusion, sold as concentrated extract supplements, purified to single catechins such as EGCG, and the source of an FDA-approved botanical drug. Value came from isolating, characterizing and testing a defined molecule, not from selling the traditional preparation.
Show the table (4 rows)
| Category | What it is | U.S. route to market | Evidence before marketing | Green tea example |
|---|---|---|---|---|
| Traditional preparation | Infusion, decoction or powder prepared as customarily used | Usually a conventional food | Food safety law; no efficacy review | Green tea infusion: EFSA estimates 90–300 mg/day EGCG at mean intake |
| Botanical dietary supplement | Extract or powder sold in a dosage form under DSHEA | No premarket approval; NDI notification only for a new dietary ingredient | Safety basis if new; claim substantiation; Part 111 manufacturing | Extract supplements supply 5–1,000 mg/day EGCG; at least 800 mg/day raised serum transaminases in trials (EFSA 2018) |
| Isolated natural compound | A single purified or chemically modified constituent | A supplement ingredient only if it qualifies as a dietary ingredient and is not excluded (often requiring an NDI notification); a new drug for a disease use. FDA does not treat highly purified substances as botanical drugs | NDI safety basis for a supplement use; full drug development for a drug use | EGCG as a single purified substance |
| FDA botanical drug | A drug product that includes or is derived from plant materials, approved through an NDA or BLA | IND, controlled trials, NDA or BLA | Substantial evidence of effectiveness and safety; batch-to-batch consistency of a complex mixture | Veregen (sinecatechins), a partially purified water-extract fraction of green tea leaves, approved in 2006 for external genital and perianal warts |
EFSA ANS Panel. Scientific opinion on the safety of green tea catechins. EFSA J. 2018;16(4):e05239. FDA, What Is a Botanical Drug? (content current as of September 3, 2026). Veregen prescribing information (indication and drug substance description). FDA, Botanical Drug Development: Guidance for Industry (Revision 1, December 2016).
Use is not proof of safety or of effectiveness
- Substitution: Aristolochia fangchi substituted for Stephania tetrandra in Belgian slimming pills caused renal fibrosis; 18 of 39 patients who underwent prophylactic surgery had urothelial carcinoma. Nortier et al. 2000, N Engl J Med
- Toxic metals: lead, mercury or arsenic in 20.7% of 193 Ayurvedic medicines bought online, made in the U.S. and India. Saper et al. 2008, JAMA
- Idiosyncratic liver injury: in ten turmeric cases from the U.S. Drug-Induced Liver Injury Network, 7 patients carried HLA-B*35:01, and 3 of the 7 products tested contained piperine. Halegoua-DeMarzio et al. 2023, Am J Med
FDA's NDI guidance treats history of use as evidence only when it is documented: relied on alone, it "generally recommends 25 years of widespread use to be the minimum", for the same material at comparable intake.
Documented harms and what each changed are on Lessons learned.
Academy: from plant record to molecule · natural products among approved drugs (Course 1)
Better absorption is measurable but is not efficacy, and anything that raises exposure at the same dose shrinks the safety margin
- Solubility or dispersibilitySolubility; droplet or particle size. Dispersing an active does not dissolve it.
- BioaccessibilityINFOGEST in vitro digestion. Released in the gut lumen, not yet absorbed.
- Absorption, FaPermeability; human PK. Crossing the gut wall.
- First-pass escape, Fg · FhGut-wall and liver metabolism, where many botanical actives are conjugated.
- Bioavailability, F = Fa · Fg · FhHuman PK: AUC, Cmax. Rate and extent reaching the circulation.
- Exposure at the targetConcentration of the active form where it acts; exposure-based safety review.
- Pharmacodynamic activityBiomarker or mechanism response at that exposure.
- Clinical efficacyControlled human trials, only for the claim and dose studied.
Text version of the two examples
Concentration changes the margin: green tea catechins
EFSA estimated mean EGCG intake from green tea infusions at 90–300 mg/day, with high consumers up to 866 mg/day, and found supplements supplying 5–1,000 mg/day. It concluded that intakes of at least 800 mg/day from supplements increased serum transaminases in intervention trials. The plant is the same; the dose and form differ.
EFSA ANS Panel. EFSA J. 2018;16(4):e05239.Absorption gains and margins move together
If a margin of 1,000 had been established on an exposure basis for a native ingredient, the same dose in a form with 10 times the systemic exposure would leave a margin near 100, assuming linear kinetics and the same active form. With the 185-fold ratio reported for micellar curcumin, the reduction would be larger still. This is why EUTECNIQ would pair every bioavailability claim with an exposure-based safety review.
Reference points and margins →EUTECNIQ would pair every bioavailability claim with an exposure-based safety review.
Explanation, details and sources
Each link in the chain has its own measurement; skipping a link is how bioavailability claims go wrong. Worked numbers, including the published curcumin formulation data, are on Bioavailability by design.
A margin of exposure divides a toxicity reference point (NOAEL or BMDL) by the estimated human intake. If a new form raises systemic exposure at the same dose, the exposure-based margin falls by that factor, unless the reference study is repeated with the new form or exposure is measured in both.
Published curcumin exposure ratios, each relative to its own study's comparator
These ratios cannot be ranked against one another: doses, subjects, comparators, analytical methods and analytes differ, in particular whether free curcumin or total curcuminoids after enzymatic deconjugation were measured. Stohs et al. (2020) describe hydrolysis of plasma samples as a widely used but inappropriate practice for quantifying the active form, and Cuomo et al. (2011) detected only phase-2 metabolites.
Micellar curcumin vs native powder, AUC of total curcuminoids
Schiborr et al. 2014 (n = 23)Hydrophilic-carrier formulation vs standardized curcumin in the same study
Jäger et al. 2014Phytosome formulation vs standardized curcumin in the same study
Jäger et al. 2014Phospholipid formulation vs standardized curcuminoid mixture
Cuomo et al. 2011Schiborr C et al. Mol Nutr Food Res. 2014;58(3):516–527. Jäger R et al. Nutr J. 2014;13:11. Cuomo J et al. J Nat Prod. 2011;74(4):664–669. Stohs SJ et al. Molecules. 2020;25(6):1397.
Dose, form and genetic susceptibility in documented harms: Lessons learned. Reference points and margins: Toxicology.
In human studies, botanicals raised or lowered the exposure to a co-administered drug by up to several-fold
Show data
| Botanical | Drug | Exposure change | Study |
|---|---|---|---|
| Green tea, 700 mL/day for 14 days | Nadolol 30 mg | AUC0–48 −85.0%; Cmax −85.3% | Misaka et al. 2014 (n = 10 healthy volunteers) |
| St John's wort | Indinavir | AUC −57% (mean; SD 19) | Piscitelli et al. 2000 (healthy volunteers) |
| Goldenseal, 14 days | Midazolam 8 mg | AUC0–∞ 107.9 → 175.3 ng·h/mL (+62%) | Gurley et al. 2008 (n = 16 healthy volunteers) |
| Grapefruit juice | Felodipine 5 mg | Bioavailability 284% of water (range 164–469%), i.e., +184% | Bailey et al. 1991 (n = 6 men with borderline hypertension) |
Inhibitors of first-pass metabolism raised drug exposure; inducers such as St John's wort lowered it.
Explanation, details and sources
Botanicals can raise or lower drug exposure several-fold
Inhibitors of first-pass metabolism, such as grapefruit furanocoumarins or goldenseal alkaloids, raise exposure. Inducers lower it: hyperforin from St John's wort binds the pregnane X receptor (Ki 27 nM) and induces CYP3A4 in human hepatocytes (Moore et al. 2000).
EUTECNIQ would offer a systematic interaction program following the NaPDI Center's recommended approaches (Paine et al. 2018) and the ICH M12 framework (2024): in vitro enzyme and transporter screens, static and physiologically based pharmacokinetic models, and partner-run clinical studies.
Evidence is coded by type: human study, in vitro or modeling, animal, or proposed mechanism. The OATP1A2 mechanism for the green tea–nadolol interaction is proposed by the authors ("possibly in part"), not proven.
Service: proposalMoore LB et al. Proc Natl Acad Sci U S A. 2000;97(13):7500–7502. Paine MF, Shen DD, McCune JS. Drug Metab Dispos. 2018;46(7):1041–1045. ICH M12 Drug Interaction Studies (FDA final guidance, August 2024).
Botanical risk spans the whole lifecycle; four hazard types are mapped across five stages in one framework
| Hazard type | Origin and cultivation | Harvest and storage | Extraction and processing | Formulation and product | Use by consumers |
|---|---|---|---|---|---|
| Intrinsic chemical hazards | Chemotype and species variation | Constituent loss or degradation | Extraction concentrates actives and toxicantsEGCG ≥ 800 mg/day raised ALT (EFSA 2018) | Higher exposure from absorption enhancersTurmeric cases: 3 of 7 products with piperine | Idiosyncratic liver injury; genetic susceptibilityHLA-B*35:01 in 7 of 10 (DILIN) |
| Extrinsic contamination and adulteration | Wrong species; soil metals; pesticidesAristolochia substitution | Molds, mycotoxins; co-harvested pyrrolizidine-alkaloid weedsPA exposure concern (EFSA 2017) | Residual solvents; economic adulterationGinkgo: 3 of 8 spiked | Undeclared drug adulteration776 products, 2007–2016 | Counterfeits and diversion |
| Exposure and interaction | No specific hazard mapped | No specific hazard mapped | Dose per serving set by the process | Release rate and dosage form | CYP and transporter interactions; vulnerable groupsIndinavir AUC −57% |
| Process and manufacturing | Supplier qualification; traceability | Drying and storage conditions | Process parameters; cleaning; cross-contact | Specification failuresTop Part 111 citation, FY2025: 111.70(e) | Shelf-life drift |
Explanation, details and sources
Red tags are documented cases. Evidence supports neither a pure-contamination nor a pure-intrinsic explanation of botanical harm, so both are controlled.
About 8% of phase 1 drug programs reached approval in 2011–2020, and FDA lists four approved botanical drug products
Show data
| Transition | Rate | Cumulative from Phase 1 |
|---|---|---|
| Phase 1 → 2 | 52.0% | 52.0% |
| Phase 2 → 3 | 28.9% | 15.0% |
| Phase 3 → filing | 57.8% | 8.7% |
| Filing → approval | 90.6% | 7.9% |
| Product (active) | Application | Approved | Use |
|---|---|---|---|
| Veregen (sinecatechins) | NDA 021902 | 2006 | External genital and perianal warts, topical |
| Fulyzaq, later Mytesi (crofelemer) | NDA 202292 | 2012 | Diarrhea in people with HIV/AIDS on antiretroviral therapy, when not caused by infection |
| NexoBrid (anacaulase-bcdb) | BLA 761192 | 2022 | Eschar removal in adults with deep partial-thickness or full-thickness thermal burns |
| Filsuvez (birch triterpenes) | NDA 215064 | 2023 | Wounds of dystrophic and junctional epidermolysis bullosa, from 6 months of age |
Explanation, details and sources
IND-enabling science and partners, not a self-funded pipeline
EUTECNIQ does not own a therapeutic pipeline. Its proposed role is the early part of drug development: characterization, mechanism and pharmacology screens, nonclinical safety under ICH M3(R2), and chemistry, manufacturing and controls (CMC) packages for an IND, sold as services or co-developed. Clinical development would be partner-funded.
The order of events matters. Under FD&C Act section 201(ff)(3)(B), an article first authorized for investigation as a new drug, with substantial clinical investigations made public, is excluded from the dietary supplement definition unless it was marketed as a food or supplement first. In letters of September 29, 2025, FDA concluded that NMN is not excluded because it was marketed as a supplement before that authorization. The route is decided for each candidate before any IND.
Roles: proposalTrial design, sample-size calculators and published botanical trials are on Clinical research.
Mapping the evidence for an ingredient?
EUTECNIQ proposes evidence maps that separate what is established, what is plausible and what is untested, with the certainty of each human finding stated.